

PsA Beyond the Joints: Rheum, Derm, and Gastro Perspectives
 8-minute watch
Dr. Saakshi Khattri is joined by a dermatologist and a gastroenterologist to discuss when skin and gut symptoms may prompt the need for multidisciplinary care in PsA
Meet the experts

Saakshi Khattri, MD
Rheumatologist, Dermatologist, and Internist
Icahn School of Medicine at Mount Sinai
New York, NY

Ahmad Amin, MD
Dermatologist
Associate Professor
Northwestern University Feinberg School of Medicine
Chicago, IL

Joshua Steinberg, MD
Gastroenterologist
Director of IBD
Gastroenterology of the Rockies
Denver, CO
Multidisciplinary care can benefit your patients with PsA

PsA is a complex, heterogeneous disease with clinical manifestations that can impact the skin and gut1,2

GRAPPA and EULAR recommend multidisciplinary collaboration when PsA extends beyond the joints1,3

Studies have shown that cross-specialty collaboration can result in prompt diagnosis and improved treatment outcomes, including more effective management of difficult-to-diagnose or uncontrolled disease and better HRQoL for patients4,5
Collaboration can fit your practice:
Whether it’s a shared clinic, referral note, or virtual consult, multidisciplinary PsA care starts with recognizing when another specialty perspective may help

Dermatology visits could open the door to earlier PsA recognition
Why joint symptoms matter in PsO
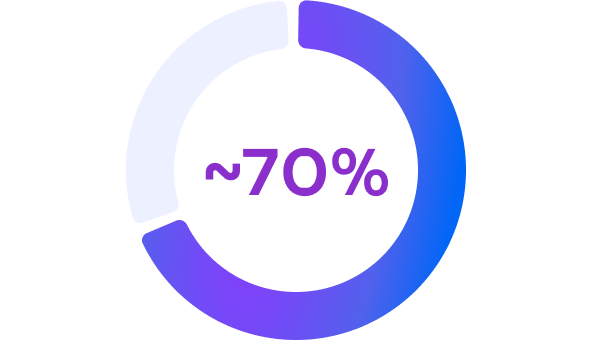
of PsA cases are
preceded by PsO6

PsA and PsO share overlapping inflammatory cytokines7–9
PsO may be the first clue to PsA. In this short discussion, Dr. Khattri and Dr. Amin discuss what rheumatologists and dermatologists can learn from each other to help manage PsA.
Watch for:

Risk factors

Screening recommendations

Shared learnings

We really need to ... ask every patient who has psoriasis about their joints.
Dr. Amin


In your current practice, how often do you comanage your patients with PsA with a dermatologist?

Skin involvement may be the first chapter, but the PsA story can also involve the gut
Recognizing the joint–gut connection in PsA and IBD
There exists a close, reciprocal connection between gut and joint inflammation10

of patients with PsA have subclinical gut inflammation,10 which may progress to IBD11

of patients with IBD develop peripheral arthritis10
There are inflammatory cytokines that play a role in both PsA and IBD7-9
Your patients with PsA may not share GI symptoms unless asked. Dr. Khattri and Dr. Steinberg discuss why rheumatologists should probe for IBD signals during PsA visits and when collaboration with gastroenterologists may be warranted.
Watch for:

GRAPPA IBD criteria

GI inflammation screening

Treatment considerations
Based on GRAPPA recommendations, Dr. Steinberg suggests rheumatologists ask their patients with PsA these questions:

Have you been having chronic diarrhea for at least 3 months?

Do you have any signs of rectal bleeding that aren’t easily explained by hemorrhoids?

Have you experienced unexplained chronic abdominal pain or unexpected weight loss?
How often do you take GI symptoms into account when considering treatment options for your patients with PsA?

When clinicians have limited access to specialists or communication is fragmented, Dr. Amin and Dr. Steinberg recommend building a trusted network of specialists who are accessible and can collaborate to manage PsA beyond the joints.
Key takeaways

As PsO often precedes PsA, dermatologists are well positioned to identify early signs of PsA such as joint pain and stiffness
At PsA visits, ask about family history of IBD, chronic diarrhea, nocturnal symptoms, rectal bleeding, chronic abdominal pain, and perianal symptoms
By comanaging patients, clinicians can deliver more coordinated, comprehensive care that supports better patient outcomes
What collaboration step feels most realistic in your practice?
Abbreviations
EULAR, European Alliance of Associations for Rheumatology; GI, gastrointestinal; GRAPPA, Group for Research and Assessment of Psoriasis and Psoriatic Arthritis; HRQoL, health-related quality of life; IBD, inflammatory bowel disease; PsA, psoriatic arthritis; PsO, psoriasis.
References:
- Coates LC et al. Nat Rev Rheumatol. 2022;18(8):465-479.
- Novelli L et al. Front Med (Lausanne). 2021;8:737079.
- Gossec L et al. Ann Rheum Dis. 2024;83(6):706-719.
- Luelmo J et al. Reumatol Clin. 2014;10(3):141-146.
- Luchetti MM et al. Clin Rheumatol. 2018;37(10):2741-2749.
- Zabotti A et al. Ann Rheum Dis. 2023;82(9):1162-1170.
- Ritchlin CT et al. N Engl J Med. 2017;376(10):957-970.
- Krueger JG et al. Front Immunol. 2024;15:1331217.
- Schett G et al. N Engl J Med. 2021;385(7):628-639.
- Scher JU. J Rheumatol Suppl. 2018;94:32-35.
- Rudbaek JJ et al. Nat Rev Gastroenterol Hepatol. 2024;21(2):86-100.
We value your feedback
Was this article helpful?
The AbbVie Medical Affairs + Health Impact department of AbbVie Inc. is the copyright owner of this presentation and has paid RheumNow to host this content. AbbVie is solely responsible for all written content within this presentation.
© 2026 AbbVie Inc. All rights reserved.